22 September 2026
Table of Contents
Once the medical plan for your child’s bone marrow transplant is in place, a quieter question often follows: how do I help my child cope with all of this emotionally? Here’s the honest answer: there’s no need to have perfect words ready. Children are remarkably resilient when they feel informed, included, and reassured — and small, steady efforts from you make a real difference.
Let’s walk through this together. This guide offers practical, age-appropriate ways to prepare your child emotionally for what lies ahead, from the weeks before admission through recovery at home.

Why Emotional Preparation Matters as Much as Medical Preparation
A bone marrow transplant involves a long hospital stay, unfamiliar procedures, and a period of feeling unwell — all of which can be frightening for a child, especially without context. Children who understand, in age-appropriate terms, what is happening and why, tend to cope better with the physical demands of treatment and recover a sense of control more quickly.
This isn’t about shielding your child from the reality of treatment, but about presenting it honestly, calmly, and in language they can hold onto.
How to Talk to Your Child, by Age Group
What your child needs to hear — and how much detail helps rather than overwhelms — changes considerably with age.

Young children (roughly under 6) respond best to simple, concrete language and comfort objects. Explaining the hospital stay as a place where “doctors will help your body get strong again,” paired with a familiar toy or blanket, often does more than a detailed explanation.
School-age children can usually handle more detail and often want to know the “why” behind procedures. Many respond well to picture books, simple diagrams, or a hospital tour if one is offered, and appreciate having some say in small decisions during their stay.
Teenagers typically want honesty, privacy, and to be included in decisions about their own care wherever possible. They may process things through questions asked days later, through friends, or not at all in front of you — all of which is normal.
Common Emotional Reactions to Expect
It’s normal for children to show a wide range of reactions in the lead-up to and during transplant — fear, anger, withdrawal, unusual clinginess, or acting out are all common and not signs that something is going wrong with your parenting or their coping.
KEY FACT
Regression — a younger child suddenly wanting a bottle again, or an older child wanting to sleep in your bed — is a common and temporary response to medical stress, not a setback.
Try not to take these reactions personally, and resist the urge to correct or minimise them. Naming what you notice — “it seems like you’re feeling worried” — often helps more than reassurance alone.
Practical Ways to Prepare Before Admission
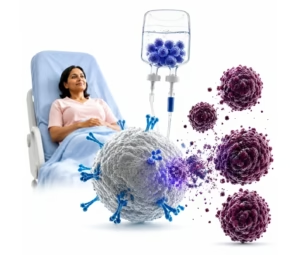
Understanding the process ahead can make it feel far less overwhelming. Here’s what the typical CAR T journey looks like:
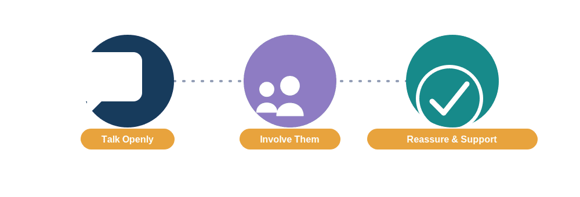
- Use honest, simple language. Avoid euphemisms that might confuse or frighten more than the truth would — for example, “medicine that fights sickness” is clearer than vague reassurances.
- Involve your child in preparation. Let them help pack a hospital bag, choose a comfort item, or ask the care team questions directly, where appropriate for their age.
- Rehearse what to expect. Many centres offer a pre-admission tour or picture book describing the ward, which can meaningfully reduce first-day anxiety.
Supporting Your Child During the Transplant Itself
Once admitted, your presence and consistency matter more than any particular technique. Many paediatric centres have child life specialists trained specifically to help children process medical experiences through play, distraction techniques, and age-appropriate explanation — it’s worth asking what’s available.
Keeping a simple, predictable daily rhythm — even something as small as a consistent morning greeting from you — can anchor a child through days that otherwise feel unpredictable.
Helping Your Child After Discharge
Emotional processing doesn’t end when the hospital stay does. Some children display delayed reactions weeks or months later, once the acute medical crisis has passed and there’s more space to process what happened. Continued gentle conversation, patience with mood changes, and a gradual return to normal activities all support this transition.
When to Seek Extra Emotional Support
IMPORTANT
If your child shows persistent sadness, ongoing sleep disruption, a return to withdrawal weeks after discharge, or if you’re finding it hard to cope yourself, it’s worth asking your care team about paediatric psychology or counselling support — these are common, not a sign of failure.
Many paediatric hemato-oncology teams have psychosocial support built into standard care. Asking about it early means support is in place if and when you need it, rather than scrambling to find it during a harder moment.
Frequently Asked Questions
Not necessarily everything at once, but age-appropriate honesty tends to build more trust than withheld information, which children often sense anyway. Your care team can help you calibrate what to share and when.
Not usually. Many children process privately or through play rather than conversation. Keeping the door open without pressure, and offering alternative outlets like drawing or a child life specialist, is often more effective than direct questioning.
Yes, this is common, particularly in school-age children and teenagers, who may direct frustration at the person who feels safest. It generally isn't a reflection of your relationship overall.
Many centres support sibling involvement in some form, recognising that siblings process the experience too. Ask your care team what's possible at your specific centre.
Parents supporting a child through transplant often neglect their own needs. Connecting with other parents who've been through a similar experience, or accessing counselling support yourself, can make a genuine difference to how you and your child cope together.
This varies by age and individual. Younger children may retain fragments rather than a full narrative, while older children and teens often remember more clearly. How the experience is framed and discussed afterward can shape how it's remembered.
A Final Word
Preparing your child for a bone marrow transplant, emotionally as well as medically, is one of the hardest things a parent can be asked to do. What this means for you is that you don’t need to get it perfect — steady honesty, involvement, and reassurance, offered imperfectly and repeatedly, are exactly what most children need to get through this experience.
If you’d like more guidance specific to your child’s age and situation, speaking with your paediatric hemato-oncology team or a child life specialist can help you find an approach that fits your family.